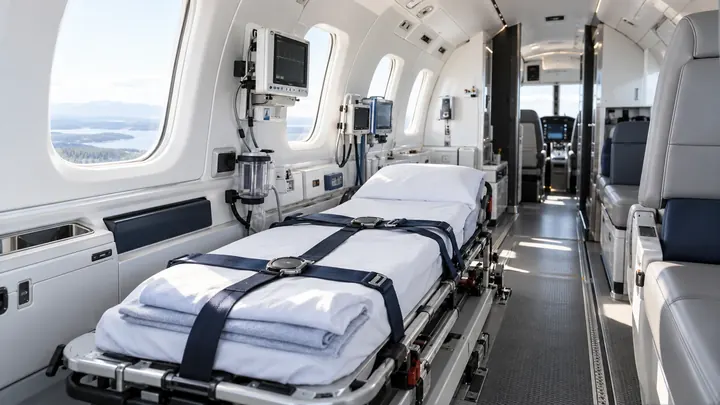
A medical interior can meet an attractive visual brief while leaving the team with awkward access or unclear equipment arrangements. An owner commissioning a cabin should involve qualified clinical and aviation specialists in evaluating the work the space must support. The assessment concerns the actual configuration and service scope, rather than the aircraft family’s general reputation.
Start with representative tasks
Clinical leadership should identify the work and handovers relevant to the intended mission, with patient groups and limitations defined. The operator and engineering specialists assess the aircraft interfaces under applicable requirements. WHO medical evacuation guidance addresses the relationship between medical equipment and transport systems. A hypothetical team should evaluate its proposed equipment arrangement using appropriate training scenarios before relying on it for service. This article provides no clinical procedure or installation specification. The commercial requirement is to fund a review that can expose a mismatch between the selected layout and the work the responsible providers intend to perform.
Review integration beyond floor space
Access, restraint, equipment interfaces, power, weight and balance and maintenance implications require specialist assessment. FAA’s Weight and Balance Handbook and EASA’s STC material provide relevant primary technical context within their scopes. A component fitting physically does not establish an approved or usable installation. A hypothetical owner adding another cabinet may alter access or other design assumptions even if total cabin dimensions remain unchanged. The project should preserve the reviewed configuration and route proposed changes through the responsible organisations. Commercial convenience should not turn repeated small alterations into an unassessed different medical cabin.
Test transitions and communication
Evaluate how the team enters, transfers authorised equipment, communicates and completes the intended handovers using approved training arrangements. Include realistic interfaces with ground providers and the receiving team. A hypothetical successful cabin demonstration with supplier staff may not reveal how the actual clinical team uses the space and records. The assessment should capture observations, limitations and actions without claiming a training exercise proves every future mission safe. Assign each issue to the appropriate clinical, engineering or operating owner. That avoids treating an ergonomic concern as merely a cosmetic preference or expecting one discipline to sign off another’s responsibility.
Keep the configuration supportable
The ownership budget should include inspection, maintenance, replacement equipment compatibility and access to relevant design and operating information. Establish who approves substitutions when a device becomes unavailable. A hypothetical replacement item sourced during a mission should not enter the configuration solely because its commercial function appears similar. Qualified review determines suitability. Investors can then assess a defined medical-transport asset with continuing obligations, rather than an interior photograph. A team-tested, documented configuration gives the operator a clearer basis for readiness and gives the owner evidence to preserve through maintenance, leasing and any later change in service scope.