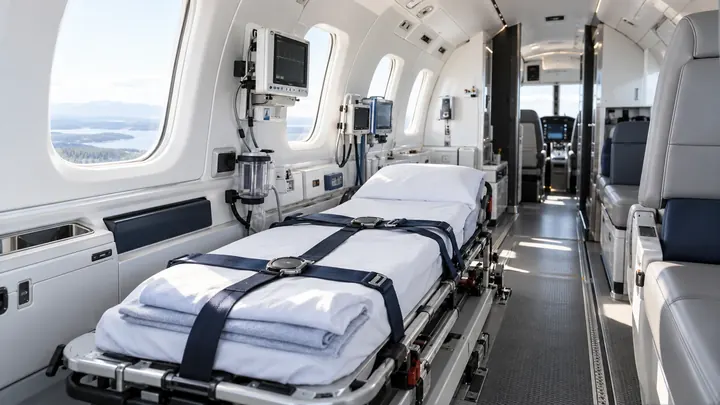
A flight radius says how far an aircraft may travel under stated conditions. It says little about where a patient can receive the required care. For an asset owner considering a medical transport base, destination capability deserves the same attention as aircraft reach. The service area's practical boundary is set by an accepted route to treatment.
Build a capability register
Record the clinical services relevant to the proposed mission types, their operating arrangements and the route for confirming availability. A general statement that a destination is a hospital conceals meaningful differences between emergency assessment, definitive specialist treatment and ongoing critical care. The register should identify the people or functions authorised to confirm acceptance.
WHO's quality health services planning guide places facility action within district and national systems. That approach supports looking beyond a single institution's facilities to the arrangements linking it with other providers.
Check the arrival pathway
A destination airport and a hospital can be near each other on a map while still presenting a difficult transfer. Assess ground transport availability, access arrangements, communications and the handover location. Hospital arrival should mean a receiving team is ready to assume care through the agreed process.
For a proposed base investment, trace representative journeys at the times the service intends to operate. Daytime site visits alone may miss the coordination problems that appear when particular teams or access points are unavailable.
Understand conditional acceptance
Acceptance may depend on the patient's needs and the receiving facility's current capacity. A partnership agreement should explain how that decision is obtained, recorded and rechecked when circumstances change. It should also identify who coordinates an alternative if the original destination can no longer receive the patient.
This is why a long partner list can be less useful than a smaller, tested network. The assessment concerns the dependability of arrangements for defined cases, not the prestige or number of institutions named.
Plan the route beyond the first admission
Some service designs also need to address onward referral, return transport or communication back to the sending facility. Those obligations should be explicit. A purchaser may assume they are included while the transport provider has priced only the initial movement.
WHO's emergency care framework extends into early inpatient care, and its referral checklists emphasise coordinated communication and documentation. Together they provide a basis for asking where the proposed service starts, where it finishes and which organisation owns each transition.
Make geography an evidence claim
ALFA’s healthcare coordination model connects partner capability with the responsibilities set out in the applicable service agreements. Any future map of healthcare coverage should therefore be tied to documented partner capability and operating readiness. A destination can be shown as under assessment before it becomes available for referrals. That distinction gives investors a clearer view of progress and lets prospective operating partners see the remaining work behind a geographic expansion.